

Yoga Poses to Avoid With Chronic Back Pain
Yoga poses to avoid with chronic back pain: Learn which yoga poses aggravate chronic back pain, why they're risky, and safe modifications to keep.
Read More →
Last Updated: August 4, 2026
When addressing musculoskeletal pain and mobility issues, spanning joints, spine, muscles, and movement, it's crucial to understand that both chiropractic care and physical therapy focus on enhancing musculoskeletal health. Chiropractors like Dr. Elaine McNally at Chiropractic Care Clinic emphasize a diagnostic-first approach aimed at identifying the root cause of discomfort, while physical therapists concentrate on tailored exercises to improve function and aid recovery.
If you’re particularly focused on understanding the nuances between chiropractic care and physical therapy specifically for lower back pain, our detailed guide comparative insights for lower back pain offers an in-depth exploration tailored to your needs.
Here is what most guides get wrong: the debate is not about which profession is "better." It is about which intervention aligns with your specific pathology, your functional goals, and your timeline. Below, we cover the key differences in treatment approach, the evidence for lower back pain, cost and insurance realities, and the growing case for combining both.
The fastest way to orient yourself is a direct comparison before diving into the detail.
| Factor | Chiropractic Care | Physical Therapy |
|---|---|---|
| Primary focus | Spinal adjustment, neuromusculoskeletal system | Therapeutic exercise, functional recovery |
| Core technique | Spinal manipulation, joint mobilization | Strength training, manual therapy, therapeutic modalities |
| Best for | Acute joint pain, spinal misalignment, short-term relief | Chronic pain, post-surgical rehab, long-term mobility |
| Treatment duration | Often shorter initial course | Typically longer, exercise-progressive |
| Diagnostic assessment | Spinal and postural evaluation | Functional movement and strength screening |
| Insurance coverage | Varies widely by plan; often limited visits | Generally covered under most major plans |
| Preventative care | Maintenance visits common | Home exercise program focus |
| Evidence strength | Strong for acute low back pain | Strong for chronic pain and post-injury rehab |
A chiropractor is a licensed healthcare professional who specializes in diagnosing and treating disorders of the neuromusculoskeletal system, primarily through spinal manipulation and joint mobilization. A physical therapist is a licensed clinician who uses therapeutic exercise, manual therapy, and therapeutic modalities to restore movement, reduce pain, and prevent re-injury.
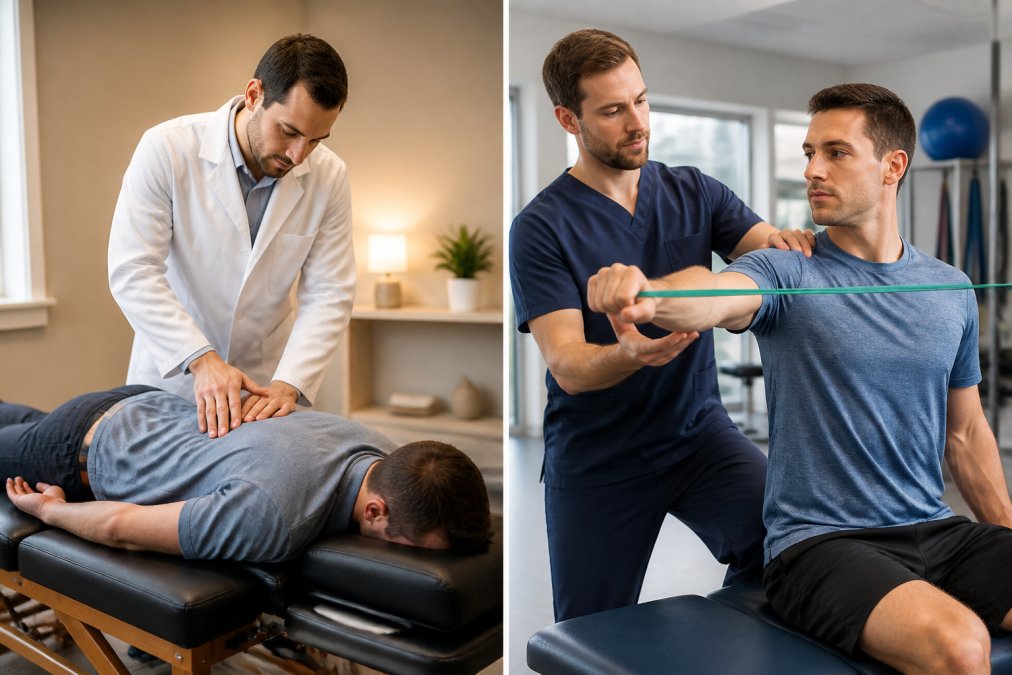
The real difference between chiropractic vs physical therapy comes down to the mechanism of change. Chiropractic targets joint mechanics and nervous system function directly through manual intervention. Physical therapy targets neuromuscular control, strength, and biomechanics through progressive loading and movement re-education. Both are legitimate, evidence-based pathways. Neither is universally superior.
Chiropractic care is built around the premise that restricted joint mobility, particularly in the spine, contributes to pain and impaired nervous system function. The primary tool is spinal manipulation, sometimes called a spinal adjustment, which applies a controlled, high-velocity force to a specific vertebral segment to restore range of motion and reduce pain signals.
Beyond the classic adjustment, modern chiropractic practice includes soft tissue massage, postural correction, lifestyle counseling, and in many clinics, rehabilitative exercise. The scope has expanded considerably over the past two decades, and many chiropractors now practice within an evidence-based framework that looks more like integrated musculoskeletal medicine than the narrow spinal-only model of earlier generations.
What chiropractic does particularly well is deliver short-term relief for acute pain. Patients with sudden-onset lower back pain, cervicogenic headaches, or restricted neck mobility often report meaningful improvement within a small number of visits. The nervous system function component is also relevant for patients whose pain presentation involves radiating symptoms or sensitivity patterns that suggest spinal nerve involvement.
Physical therapy is grounded in movement science. A licensed physical therapist conducts a diagnostic assessment that evaluates strength, range of motion, movement patterns, and functional capacity, then builds a treatment plan designed to correct the deficits driving the patient's symptoms.
The core interventions include therapeutic exercise, manual therapy, joint mobilization, neuromuscular re-education, and therapeutic modalities such as ultrasound or electrical stimulation. The distinguishing feature of physical therapy is progressive loading: the program evolves as the patient improves, building toward functional recovery rather than symptom suppression alone.
Physical therapy is the standard of care for post-surgical rehabilitation, sports injury recovery, and chronic pain conditions where structural deconditioning is a primary driver. For patients with chronic back pain who have already addressed the acute phase, strength training and biomechanical correction through physical therapy address the root cause more directly than passive manual treatment alone.
According to the American Physical Therapy Association's clinical resources, physical therapists are trained to address conditions across the entire musculoskeletal system, from acute injury through long-term rehabilitation, making the discipline particularly suited to patients with complex or multi-joint presentations.
Lower back pain is the condition where the chiropractic vs physical therapy effectiveness debate is most thoroughly studied, and the evidence supports a nuanced answer rather than a single winner.
For acute low back pain, spinal manipulation delivered by a chiropractor produces clinical outcomes comparable to other first-line treatments, including short-term pain reduction and improved mobility. The effect is most pronounced in the first four to six weeks of an episode, which aligns with the natural history of acute back pain. Patients who receive spinal manipulation early in an episode often return to function faster than those who rely on rest or medication alone.
For chronic lower back pain, the picture shifts. Chronic pain involves central sensitization, muscle deconditioning, and movement avoidance patterns that spinal manipulation alone does not fully address. Therapeutic exercise delivered through a structured physical therapy program produces more durable outcomes over a six-to-twelve-month horizon because it rebuilds the neuromuscular infrastructure that protects the spine.
The practical implication: if you have had lower back pain for years, tried multiple interventions, and are still symptomatic, a physical therapy evaluation focused on functional movement deficits is likely to identify something earlier assessments missed. If your pain is acute and severe, a chiropractor can often provide faster initial relief while you determine the longer-term plan.
As documented in clinical practice guidelines from the American College of Physicians, non-pharmacologic treatments including spinal manipulation and supervised exercise are recommended as first-line interventions for both acute and chronic lower back pain, which validates both approaches within current evidence-based practice.
Chiropractic care tends to produce the strongest results for conditions where joint restriction and nervous system irritation are the primary drivers:
Patients recovering from auto accidents often find chiropractic care particularly relevant because whiplash and related soft tissue injuries respond well to early joint mobilization and manual therapy. Seniors managing age-related joint stiffness also report benefit, though treatment techniques are typically modified for older patients with reduced bone density or comorbidities.
Physical therapy is the more appropriate first choice when the clinical picture involves functional deficits, post-surgical recovery, or chronic deconditioning:
Office workers with chronic neck and shoulder pain driven by postural dysfunction often respond better to physical therapy because the treatment addresses the movement habits and muscle imbalances that cause the problem, rather than temporarily relieving the symptoms.
Chiropractic adjustment frequency is one of the most common sources of confusion and, frankly, one of the most common sources of patient frustration. The honest answer is that frequency should be determined by your clinical response, not by a predetermined package.
A typical initial course for acute lower back pain involves several visits over two to four weeks, with frequency decreasing as symptoms improve. Many patients see meaningful improvement within six to eight visits. If you are not progressing after ten visits, the treatment plan should be re-evaluated, and a referral or co-management with a physical therapist is worth discussing.
Maintenance or preventative care visits are a legitimate option for patients who have achieved their initial goals and want to maintain spinal mobility, particularly for those with physically demanding jobs or a history of recurrent episodes. However, maintenance care should be your choice based on perceived benefit, not an automatic extension of an initial treatment plan.
A common mistake is confusing a provider's scheduling preferences with clinical necessity. Patients who ask direct questions about expected visit counts and measurable progress milestones at the first appointment tend to have better outcomes because they stay engaged in their own care.
Insurance coverage for chiropractic vs physical therapy differs in ways that materially affect out-of-pocket costs, and this is an angle that most comparison guides underserve.
Most major health insurance plans, including Medicare and many Medicaid programs, cover physical therapy when it is medically necessary and ordered by a physician. Coverage typically includes a set number of visits per year, though limits vary by plan. Physical therapy is generally categorized as a standard rehabilitation benefit, which means it faces fewer coverage restrictions than chiropractic.
Chiropractic coverage is more variable. Medicare Part B covers spinal manipulation for subluxation, but does not cover other chiropractic services such as X-rays or maintenance care. Many commercial insurance plans cover chiropractic but impose stricter visit limits, require prior authorization, or apply higher co-pays than they do for physical therapy. According to Medicare coverage information from the Centers for Medicare and Medicaid Services, beneficiaries should verify what their specific plan covers before beginning treatment, as chiropractic benefits differ significantly across plan types.
For patients whose insurance covers limited chiropractic visits, the practical approach is to use covered visits strategically during the acute phase and transition to a home exercise program or physical therapy for the maintenance phase. Patients paying out of pocket should ask providers for a clear fee schedule at the first contact. Pricing for both disciplines varies by region, provider type, and visit complexity, so direct inquiry is the only reliable way to understand your actual cost exposure.
The most clinically sophisticated answer to the chiropractic vs physical therapy effectiveness question is not a binary choice. Many patients with complex or chronic musculoskeletal conditions benefit from a coordinated plan that uses both disciplines sequentially or concurrently.

The hybrid model typically works as follows: chiropractic care addresses acute joint restriction and pain in the early phase, reducing the barrier to movement. Once the patient has adequate mobility and reduced pain, physical therapy introduces progressive therapeutic exercise to build the strength and neuromuscular control needed for long-term stability. The two providers share clinical notes and coordinate treatment goals, which produces better outcomes than either discipline working in isolation.
This integrative approach is particularly well-suited to patients recovering from auto accident injuries, patients with chronic lower back pain who have not responded to either modality alone, and athletes who need both structural normalization and performance rehabilitation. The injury prevention benefits of combining spinal adjustment with strength training are also well-supported by clinical reasoning: a mobile spine supported by strong stabilizing muscles is significantly more resilient than one that is only adjusted or only exercised.
The practical barrier is coordination. Not all providers communicate across disciplines, and insurance may treat the two services differently even within the same episode of care. Patients pursuing a hybrid approach should explicitly ask both providers whether they are willing to co-manage the case and share documentation.
Both chiropractic care and physical therapy show clinical value for back pain, and the better option depends on the nature of the problem. Chiropractic spinal manipulation tends to address acute pain and joint mobility quickly, while physical therapy focuses on strength training, postural correction, and long-term functional recovery. For chronic back pain, evidence-based guidelines often recommend a combination of manual therapy and therapeutic exercise, which means the two approaches frequently complement each other rather than compete.
Physical therapists are trained to design progressive rehabilitation programs that rebuild strength, restore range of motion, and address biomechanics over a structured recovery timeline. They also work extensively with post-surgical patients and those managing neurological conditions. While chiropractors specialize in spinal adjustment and neuromusculoskeletal function, physical therapists place greater emphasis on therapeutic exercise, injury prevention education, and helping patients maintain functional independence after treatment ends.
Both chiropractic care and physical therapy are covered under many private insurance plans and Medicare, though coverage limits, copays, and visit caps vary considerably by plan. Medicare Part B covers chiropractic manipulation for subluxation but has historically excluded other chiropractic services. Physical therapy benefits under Medicare are subject to annual financial thresholds. Patients should contact their insurer directly to confirm covered services, required referrals, and any prior authorization rules before beginning treatment.
Chiropractic adjustment frequency depends on the diagnosis, severity, and individual response to care. An acute injury may require several visits per week initially, tapering as symptoms improve. Chronic conditions often involve a longer initial phase followed by periodic maintenance visits. A qualified chiropractor should reassess progress at regular intervals and adjust the treatment plan accordingly. Patients should be cautious of any provider who cannot articulate clear recovery milestones or who recommends indefinite high-frequency visits without documented clinical justification.
Yes, and clinical guidelines increasingly support an integrated approach for musculoskeletal conditions. Spinal manipulation from a chiropractor can reduce acute pain and improve joint mobility, making it easier for patients to engage in the therapeutic exercise and strength training that physical therapy requires. Some practices coordinate care directly between providers. Patients recovering from auto accidents, work injuries, or chronic pain conditions often report better outcomes when both short-term pain management and long-term rehabilitation goals are addressed within the same treatment plan.
Chronic musculoskeletal pain rarely resolves through a single intervention, and navigating the options without a clear framework wastes time and money. Chiropracticcare.clinic provides chiropractic-focused care for patients seeking an evidence-informed starting point for spinal and neuromusculoskeletal conditions. Visit chiropracticcare.clinic to learn about available services and to take the first step toward a structured treatment plan built around your specific presentation.


